
Billers, coders and practice managers usually land on the F33.1 ICD-10 code for one of three reasons: a claim edit flagged it, an audit asked for support, or an EHR dropdown offered several depression options and someone needs to pick the right one. This guide covers what the code means, what the note has to say, and how to keep it clean on a claim.
Quick answer: F33.1 is a billable FY2027 ICD-10-CM code for major depressive disorder, recurrent, moderate. Use it when the provider documents recurrent major depressive disorder and a current episode of moderate severity. It is valid for dates of service from October 1, 2026 through September 30, 2027.
What does ICD-10 code F33.1 mean?
F33.1 sits in Chapter 5 of ICD-10-CM, which covers mental, behavioral and neurodevelopmental disorders. It falls under the F30 to F39 block for mood [affective] disorders, inside the F33 category for major depressive disorder, recurrent. The code is a complete, billable diagnosis, so no extra characters are needed.
| Item | Detail |
|---|---|
| Code | F33.1 |
| Official title | Major depressive disorder, recurrent, moderate |
| Category | F33, Major depressive disorder, recurrent (header) |
| Block | F30-F39, Mood [affective] disorders |
| Chapter | 5, Mental, Behavioral and Neurodevelopmental disorders |
| FY2027 status | Billable |
| FY2027 change | None |
| Excludes1 at F33 | Bipolar disorder (F31.-), manic episode (F30.-) |
| Inclusion terms at F33 | Recurrent episodes of depressive reaction, endogenous depression, major depression, psychogenic depression, reactive depression, seasonal affective disorder and others |
The Excludes1 note at the F33 category matters in daily work. It tells you that a recurrent depression code and a bipolar or manic code do not belong together on the same claim. The official wording comes from the CMS and NCHS ICD-10-CM tabular list, so check it there when you need to quote it.
What "recurrent" and "moderate" require in the record
Two words in the title drive the whole code: recurrent and moderate. Both have to come from the provider. Coders select from documentation. They do not diagnose, and they do not infer severity from a symptom list or a screening score. If you want the full decision on episode type, the companion guide on single versus recurrent episodes walks through it.
Recurrent
The provider has to document major depressive disorder as recurrent, meaning there has been a prior major depressive episode. The clinical criteria for separating one episode from another come from the DSM-5-TR, published by the American Psychiatric Association. Those criteria belong to the APA and to the clinician applying them. Billing teams should not paraphrase them as coding rules. Your job is to confirm the note says "recurrent" or describes a documented history of earlier episodes in clear clinical language.
Moderate (current episode)
Severity describes the current episode only. A patient who had a severe episode three years ago and is now in a moderate one is coded for the moderate one. A past severe episode does not turn the current claim into F33.2.
If the note says "recurrent depression" and never states severity, the correct code is F33.9, major depressive disorder, recurrent, unspecified. In that case a provider query may be appropriate, because a more specific code is usually better supported and tells a cleaner story to the payer. Follow the ICD-10-CM index path from major disorder, depressive, recurrent to confirm where the documentation lands.
F33.1 vs related depression codes
Most mental health billing errors in this family come from picking a neighbor of F33.1. Use the table below to check each option against what the provider actually wrote.
| Code | Title (short) | Use instead of F33.1 when the provider documents... |
|---|---|---|
| F33.0 | MDD, recurrent, mild | Recurrent MDD with a mild current episode |
| F33.2 | MDD, recurrent, severe without psychotic features | Recurrent MDD with a severe current episode and no psychotic features |
| F33.3 | MDD, recurrent, severe with psychotic symptoms | Recurrent MDD with a severe current episode and psychotic symptoms |
| F33.40 | MDD, recurrent, in remission, unspecified | Recurrent MDD in remission without stating partial or full |
| F33.41 | MDD, recurrent, in partial remission | Recurrent MDD in partial remission |
| F33.42 | MDD, recurrent, in full remission | Recurrent MDD in full remission |
| F33.9 | MDD, recurrent, unspecified | Recurrent MDD with no severity or remission status |
| F32.1 | MDD, single episode, moderate | A first and only episode of moderate severity |
| F32.A | Depression, unspecified | Depression with no further detail on type, episode or severity |
A simple habit helps here. Read the note for two answers: is this a first episode or a recurrence, and what is the severity or remission status right now? Once you have both, the code is usually clear.
Coding rules that affect F33.1 claims
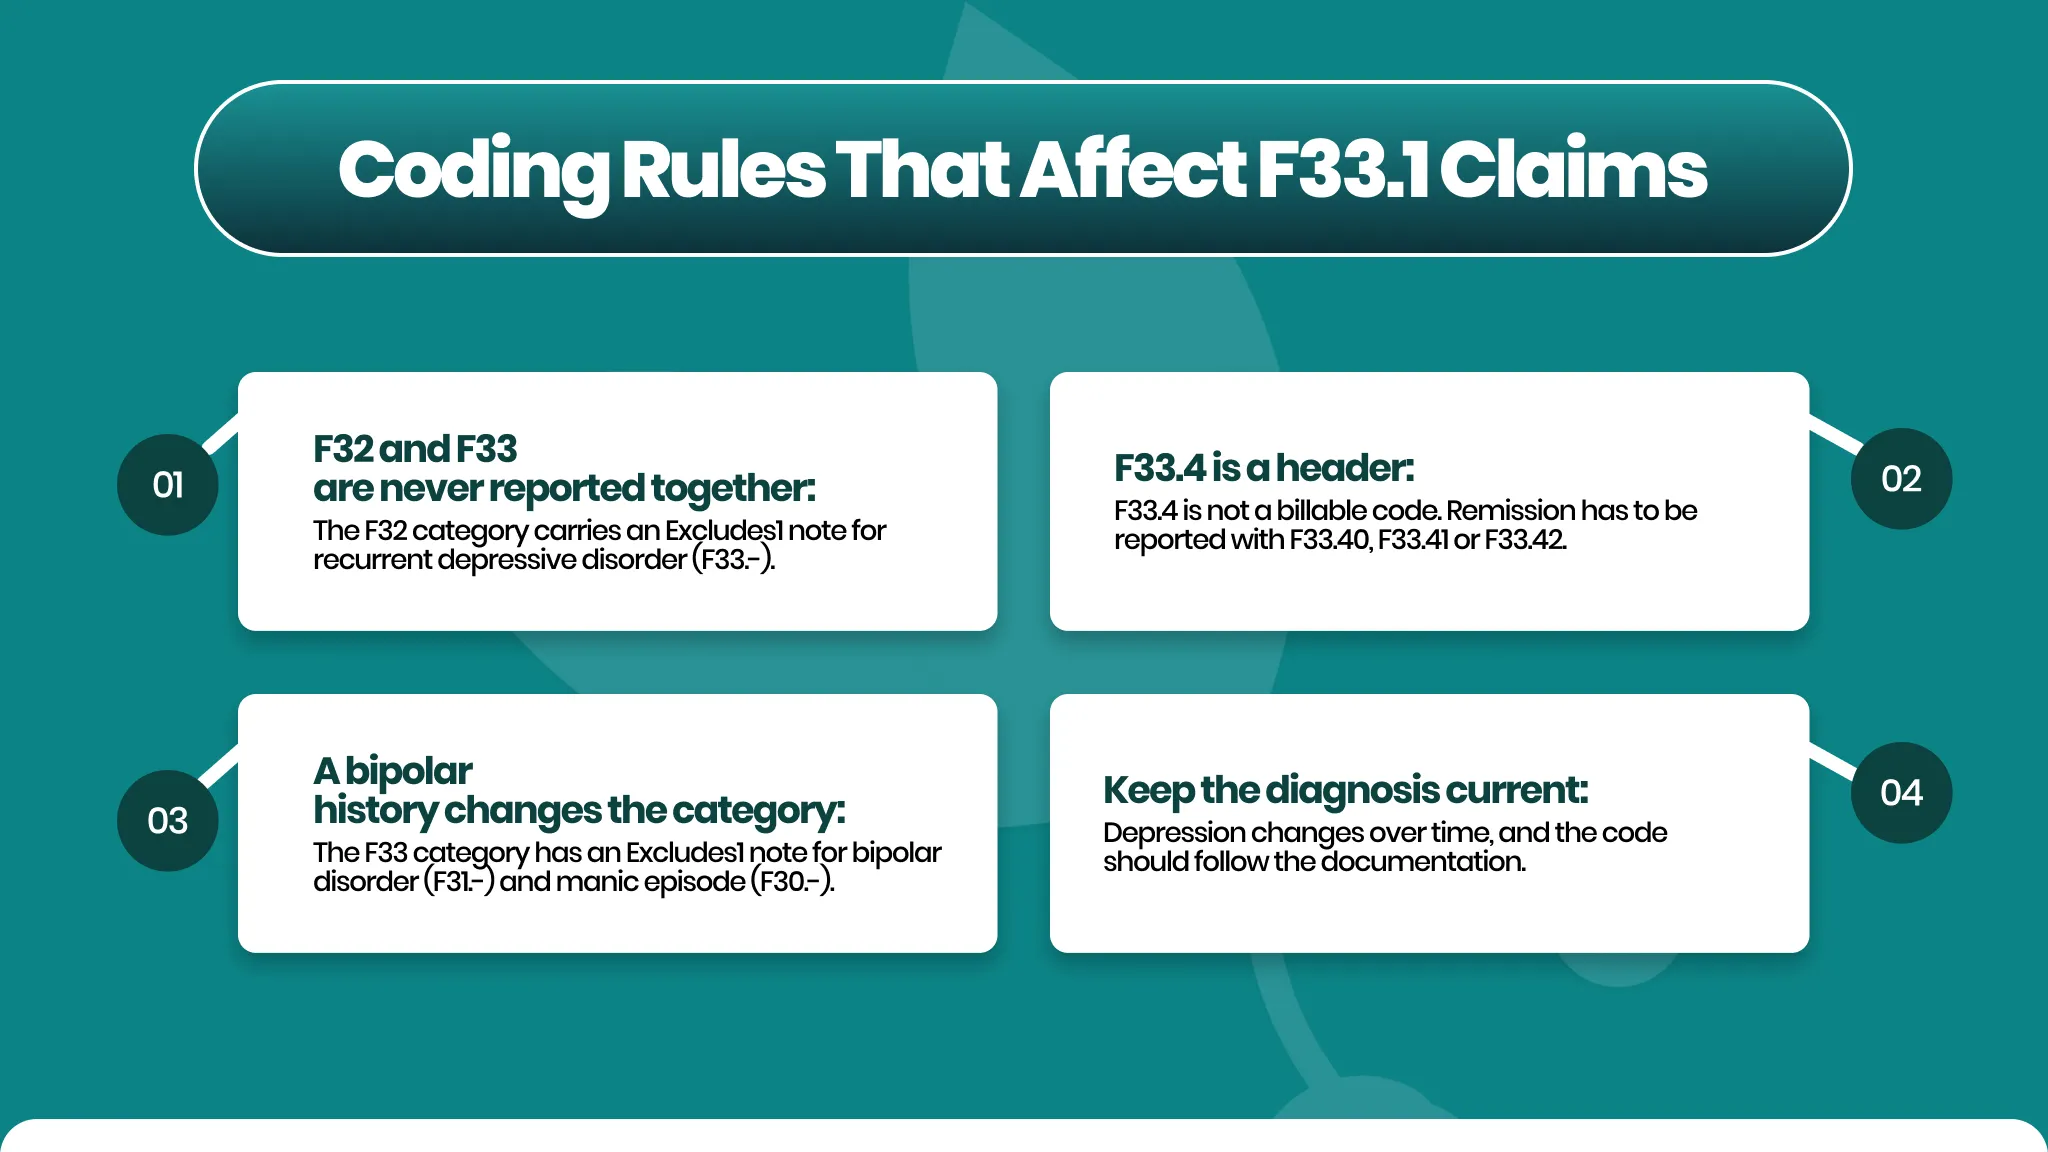
A few tabular rules cause most of the denials and audit findings tied to this code. For a wider look at how weak notes lead to rejected claims, see our post on documentation errors, medical necessity and coding audits.
- F32 and F33 are never reported together: The F32 category carries an Excludes1 note for recurrent depressive disorder (F33.-). That means a single episode code and a recurrent code should not appear on the same claim for the same condition. If the EHR carries an old F32.1 on the problem list and the provider now documents recurrence, the problem list needs updating before the claim goes out.
- A bipolar history changes the category: The F33 category has an Excludes1 note for bipolar disorder (F31.-) and manic episode (F30.-). If the record shows a manic or hypomanic history, F33.1 may not be the right family at all. That is a clinical determination for the provider, so route the question to them rather than guessing.
- F33.4 is a header: F33.4 is not a billable code. Remission has to be reported with F33.40, F33.41 or F33.42. A claim that stops at F33.4 will be rejected for lacking the required specificity.
- Keep the diagnosis current: Depression changes over time, and the code should follow the documentation. When the episode moves to partial or full remission, the provider should say so, and the code should shift to F33.41 or F33.42 at the next visit. Carrying F33.1 forward on autopilot is a common finding in audits, and it can make the record look copied rather than reviewed.
Pairing F33.1 with psychotherapy and evaluation codes
The primary question many billers ask when submitting claims is, is F33.1 billable on its own for routine mental health visits? Yes, the diagnosis directly supports medical necessity for the services a behavioral health practice bills most often: the diagnostic evaluation (90791) and individual psychotherapy at 45 minutes (90834) or 60 minutes (90837). However, using a valid F33.1 diagnosis code alone does not carry the claim. The note still has to show the session length, the intervention and the patient's response.
For billing details on each service, see our guides on how to bill CPT code 90834 and how to bill CPT code 90837. Payer policies on frequency and diagnosis pairing vary, so check each payer's current rules before you assume a combination will pay.
Two illustrative coding scenarios
These examples are simplified to show the rule and nothing more.
- Scenario A (Hypothetical): A provider's note documents major depressive disorder, recurrent, with a current episode of moderate severity, and describes two prior episodes. The documentation supports both parts of the title, so the code is F33.1.
- Scenario B (Hypothetical): A note reads "recurrent depression" with no statement of severity. The coder cannot assume moderate. The supported code is F33.9, and a query to the provider asking for the current severity is reasonable. If the provider answers moderately and updates the note, the code can change to F33.1.
Common errors and pre-claim checklist
Most F33.1 problems are small and preventable. Run through this list before a claim leaves the building.
| Check | What to confirm |
|---|---|
| Recurrence documented | The note states recurrent MDD or a prior episode |
| Severity documented | The current episode is described as moderate |
| No F32 on the same claim | Single episode codes are removed when recurrence is documented |
| No bipolar conflict | No F31.- or F30.- diagnosis conflicts with F33 |
| Not a header | Remission is coded to F33.40, F33.41 or F33.42, never F33.4 |
| Code is current | The code matches the most recent visit, not an old problem list |
| Date of service | The visit falls within the FY2027 code set window |
If you would rather not run these checks by hand on every claim, a second set of eyes helps. A short pre-bill review catches most of these issues before the payer does.
Also read
Coding support
Behavioral health coding looks simple until a denial lands. Between episode type, severity, remission status and payer rules, small documentation gaps add up fast. GreenSense Billing helps practices review notes, tighten medical coding workflows and keep depression claims clean from the first submission.
Need a second look at your behavioral health claims? Talk with the GreenSense Billing team about coding support built for mental health practices.