
A virtual scribe is usually cheaper and easier to scale, because the vendor carries recruiting, benefits, backfill and equipment. An in-house scribe still fits procedure-heavy settings, providers who want shoulder-side help, and practices where the fully loaded math comes out lower. Run both numbers before deciding.
If you are weighing virtual medical scribe vs in-house scribe, you are really choosing between two ways of buying the same thing: clean, timely notes in your EHR. One route makes you the employer. The other makes you a client.
Choose virtual if you want flexible coverage, no recruiting or backfill cycle, and a predictable service rate. Choose in-house if you need someone physically in the room doing hands-on work, or your own numbers show employment costs less. A virtual medical scribe is not the right answer for every clinic, and we will say where it is not.
Quick answer: A virtual scribe is usually cheaper and easier to scale, because the vendor carries recruiting, benefits, backfill and equipment. An in-house scribe still fits procedure-heavy settings, providers who want shoulder-side help, and practices where the fully loaded math comes out lower. Run both numbers before deciding.
Side-by-side comparison
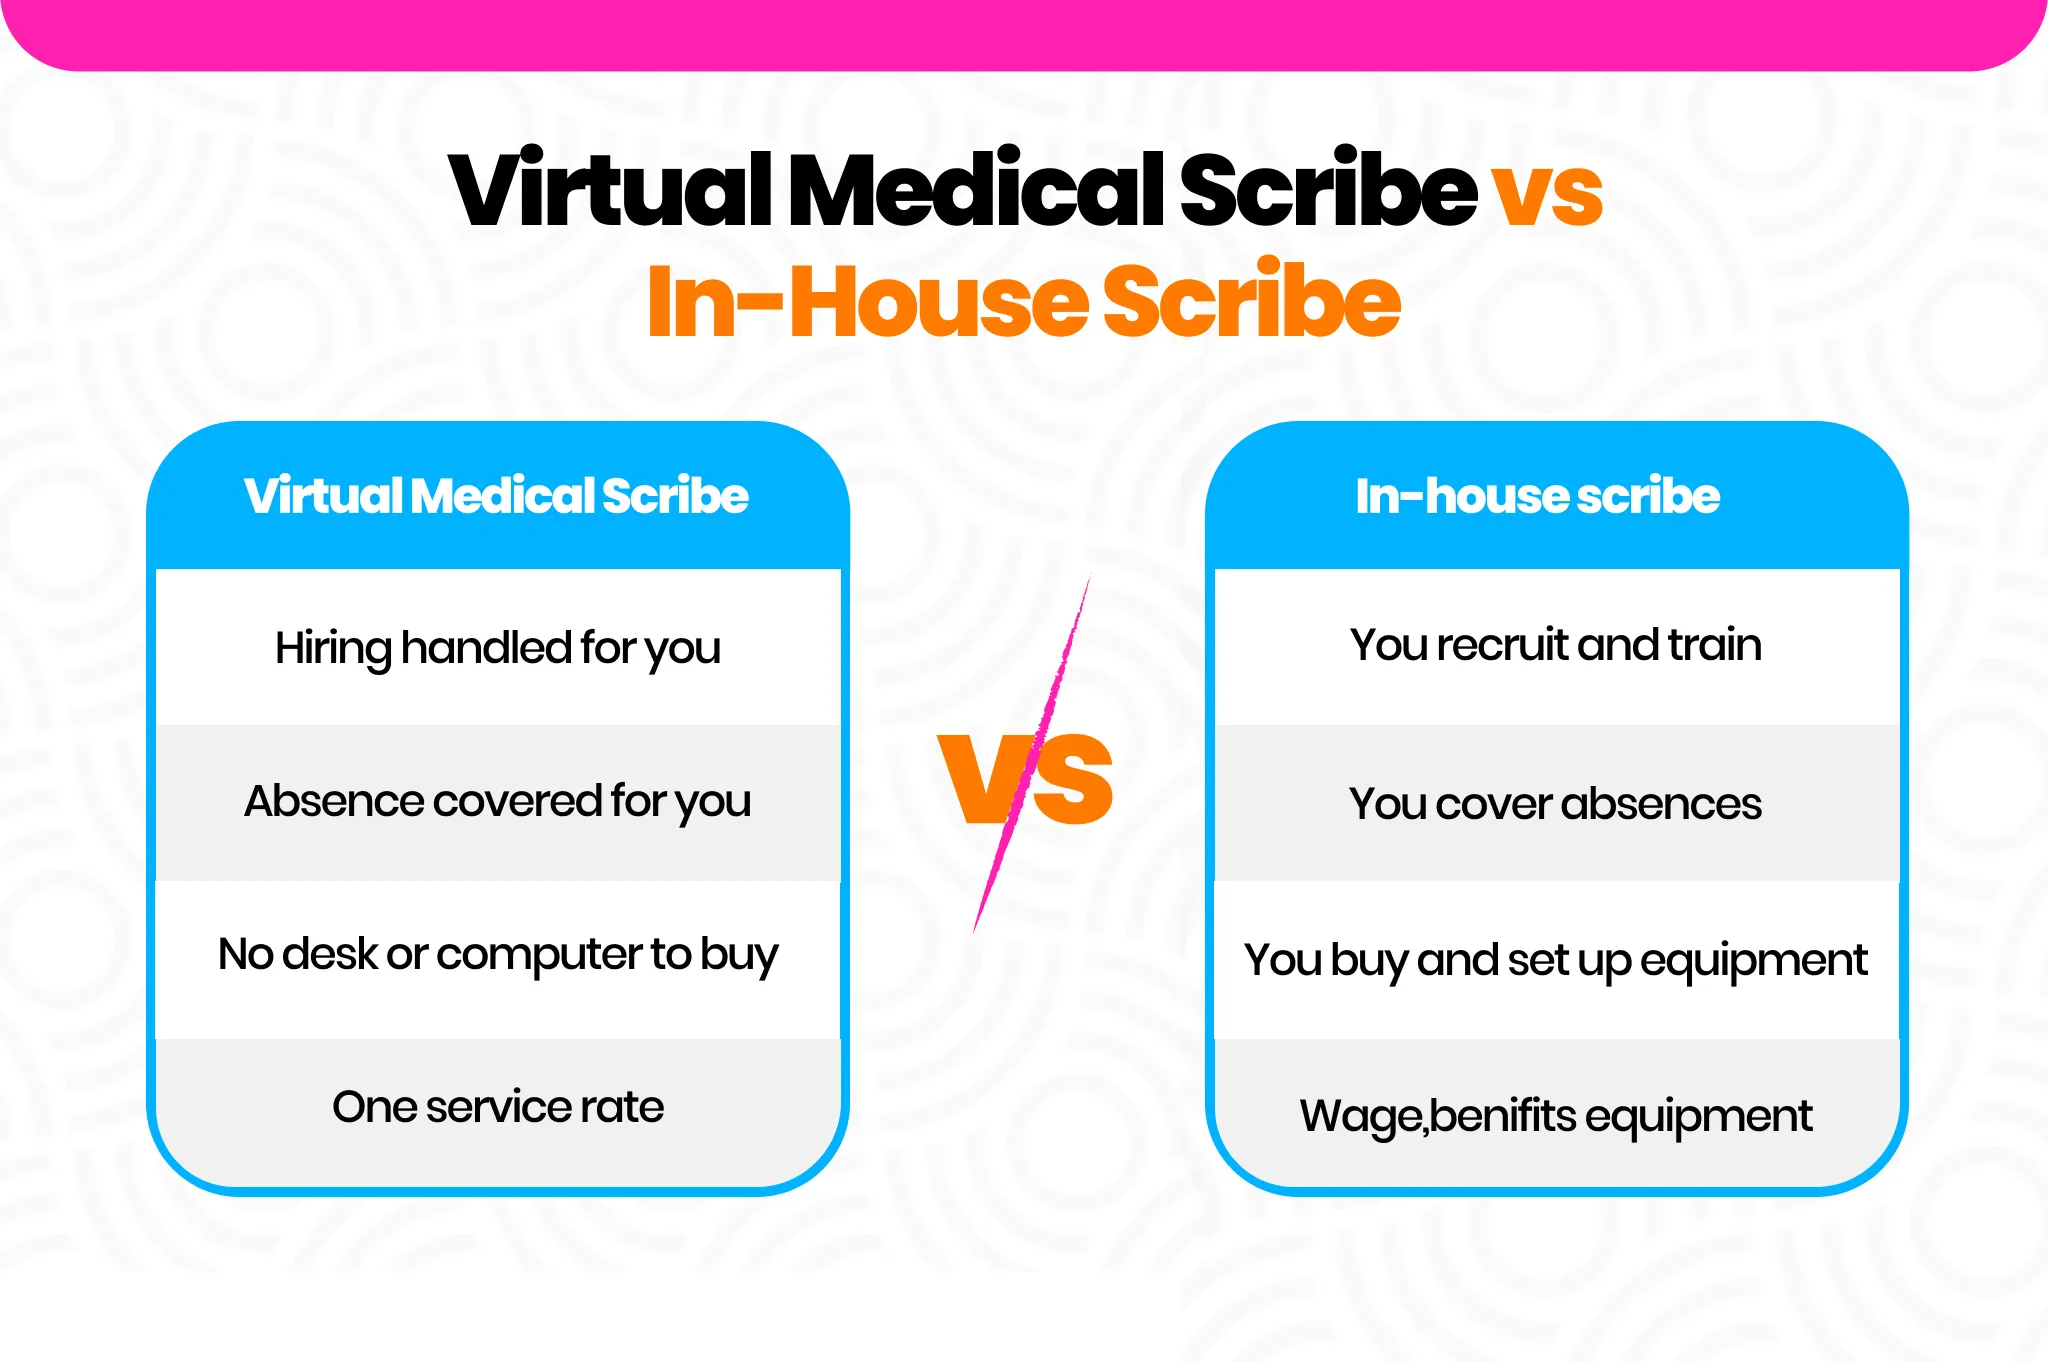
This table covers the remote scribe vs in-person scribe question across the factors practice managers ask about most.
| Factor | Virtual scribe | In-house scribe | Who it favors |
|---|---|---|---|
| Where they work | Remotely, by secure audio or video | In the exam room or office | Depends on your setting |
| Employment model | Vendor employs and manages | Your practice employs and manages | Virtual if you want less HR work |
| Cost structure | Service rate for contracted hours | Wage, benefits, taxes, equipment, overhead | Run both numbers |
| Absence and turnover | Vendor arranges coverage and replacement | You cover gaps and rehire | Virtual |
| Ramp-up | Depends on EHR access and specialty | Depends on hiring and training | Neither is automatic |
| Exam-room presence | Not physically present | Present | In-house |
| Hands-on tasks (rooming, fetching records) | Not possible | Possible | In-house |
| EHR access model | Own login, set up for a remote user | Own login as an employee | Similar |
| HIPAA status | Business associate with a BAA | Workforce member under your policies | Both workable |
Best for: Virtual suits clinics that want documentation help without adding headcount, especially across several providers or uneven schedules. In-house suits settings where the scribe also does physical tasks.
The real cost of an in-house scribe
The most common mistake in this decision is comparing a vendor's rate to an hourly wage. A wage is not the in-house medical scribe cost. The honest figure is your fully loaded labor cost, and you should build it yourself.
For the benefits piece, the BLS Employer Costs for Employee Compensation report is the right reference. It showed benefits at 30.0 percent of private-industry compensation cost in June 2026, and 31.5 percent for full-time workers. That share includes legally required benefits such as payroll taxes and workers' compensation, not only health insurance and paid leave.
We are not publishing a sample wage or a worked example, because pay varies by city and specialty and an invented number would mislead you. Use this worksheet with your own figures:
| Cost item | How to calculate it |
|---|---|
| Base pay | Hourly wage × paid hours per year |
| Benefits load | Base pay × your benefits share (BLS gives a benchmark) |
| Recruiting | Job ads, recruiter fees, interview time |
| Training ramp | Weeks of reduced output × cost of the trainer's time |
| Workstation and equipment | Computer, desk, software, supplies |
| Backfill during absence | Cost of coverage for sick days, leave and vacation |
| Turnover replacement | Cost of one rehire × how often turnover happens |
| Total fully loaded cost | Add the rows |
Be honest about the last two rows. Absences and departures are not rare events, and they hit a small practice hard. If you have lost scribes before, use your own history.
The real cost of a virtual scribe
The virtual side is simpler, but it is not free of hidden items. A fair virtual scribe cost comparison includes three lines:
- Service rate × contracted hours. Ask for a written all-in rate and what it covers.
- Practice-side setup and oversight time. Someone on your team will set up templates, review early notes and give feedback.
- EHR user license. The scribe usually needs a login of their own. Ask your EHR vendor whether an EHR user license applies and what it costs, because this is the line most buyers forget.
Compare that total with the in-house worksheet above. For how vendors typically structure pricing, see our guide on how virtual scribe services are priced. This is the clearest way to judge outsourced vs employed scribe costs for your own clinic, instead of trusting a headline percentage.
HIPAA: employee vs vendor
Privacy is where the two models actually differ in paperwork. An employed scribe is a workforce member. They are trained under your own policies, sign your confidentiality agreements and work under your direct control.
A scribe company that handles protected health information for you is a business associate. That relationship needs a signed BAA before any PHI is shared. Under HHS guidance, workforce members are not business associates, so an in-house scribe does not need a BAA, while a vendor does. Confirm the definitions on the HHS Business Associates page before you finalize your paperwork.
Neither model is automatically safer. An employed scribe still needs training and access controls. A vendor still needs a BAA, role-based access and clear breach procedures. Our upcoming post on this topic goes deeper.
Where in-house still wins
A fair comparison has to say this clearly. Some settings are better served by a person in the building.
- Procedural and surgical settings. When the provider's hands and attention are fully occupied, an in-room scribe can capture details a remote scribe may not hear or see well.
- ED-style environments. Fast, noisy settings often need hands-on help, such as rooming, fetching records or running errands between patients.
- Unreliable connectivity. A remote scribe depends on a stable connection. If your clinic cannot guarantee one, in-person is safer.
- Providers who want a person in the room. Some clinicians simply work better with someone beside them. That preference is legitimate.
A virtual scribe cannot room patients or retrieve physical records. If those tasks are a big part of your bottleneck, you may need a different kind of help altogether. Our post on virtual assistants vs front desk staff explains how to split that work.
The third option: AI or hybrid
You do not have to pick only between two human models. An ambient AI scribe listens and drafts a note automatically, with no human in the loop. That can lower the cost per note, but it shifts more review work onto the provider, who must catch errors and gaps. Human scribes bring context, template knowledge and a second pair of eyes. A 2026 comparison in the Annals of Emergency Medicine looked at human and AI scribes, and it is worth reading in full before you rely on it.
A hybrid scribe model mixes approaches. Some practices use a virtual scribe for their heaviest-charting providers and an in-person scribe in the procedure suite. Others use AI drafts for simple visits and a human scribe for complex ones. If you want a view of the clinical evidence, read the documented benefits for physicians, which includes the 2024 JAMA Network Open finding of 5.6 fewer EHR minutes per appointment with virtual scribes.
How to switch from in-house to virtual
If your worksheet points toward a vendor, a careful handover protects your providers. Use this checklist:
- Overlap the two scribes for a short period, so nothing is lost in the transition
- Hand over your note templates and specialty phrasing
- Set up EHR access and permissions for the new scribe, with their own login
- Sign the BAA before any PHI is shared
- Confirm turnaround expectations and review steps in writing
- Schedule a feedback loop with each provider in the first weeks
Ask any vendor for a written ramp plan, because speed depends on your EHR access setup and your specialty. We do not publish a promised start time, and you should be cautious of anyone who does without knowing your system.